

Industry: Healthcare and Epidemiology
Product: ModelRisk
Application: Hospital Resource Allocation — Stochastic LP for Beds, OR-Time, and Nurses
A 480-Bed Hospital Allocating Beds, OR-Time, and Nurses Under Stochastic Demand
The hospital's annual operating-plan spreadsheet — built on a deterministic linear program — said the 480-bed tertiary facility would run at 88% utilization and comfortably within capacity. The same exposure data fed through a Monte Carlo simulation said census exceeded 480 beds on roughly 3% of days, and the ICU spilled over its 28 staffed beds on 10% of days. The deterministic LP is a beautiful answer to the wrong question — it allocates against the average day. Hospitals do not live on the average day; they live on the joint draw of a flu spike, a multi-vehicle trauma, and a weekend staffing dip, and any plan that does not price that joint draw is mis-pricing the resource base.

The deterministic LP optimizes against the green line — the mean census of 420. The simulation says the 95th-percentile day sits at roughly 473 patients, and the 99th-percentile day at roughly 497 patients (a 17-bed overflow that must be absorbed by hallway boarding, transfer-out, or elective cancellation). The probability of any-day overflow is ~3% — roughly one day in a month, on average, the hospital is over its staffed bed count, a tail the deterministic plan does not show at all.
A 480-bed tertiary hospital with five service lines (ICU, Cardiac, Surgical, Medical, Maternity) rebuilt its allocation model in ModelRisk. The deterministic LP still runs nightly — it remains the right tool for the daily duty-roster — but its constraints are now stress-tested against a 100,000-iteration demand simulation before the annual capacity plan is signed.
Service-line census is over-dispersed, not Poisson
Three years of hospital census data show variance-to-mean ratios between 1.0 (Maternity) and 2.6 (Surgical). Treating each service's daily census as Poisson — which the deterministic LP implicitly does whenever it uses a single mean — understates the tail. The simulation uses a Negative Binomial per service, calibrated to the historical mean and variance:
- ICU — mean census 22, P99 ≈ 35 (well above the 28 staffed beds)
- Cardiac — mean 78, P99 ≈ 113
- Surgical — mean 125, P99 ≈ 170
- Medical — mean 155, P99 ≈ 204
- Maternity — mean 40, P99 ≈ 55
These tails are not academic. The simulation says the total inpatient demand reaches 497 patients on the worst 1% of days — 17 above the staffed bed count — even though the mean total is 420 and the deterministic plan would call that day "well within capacity."
What drives the overflow
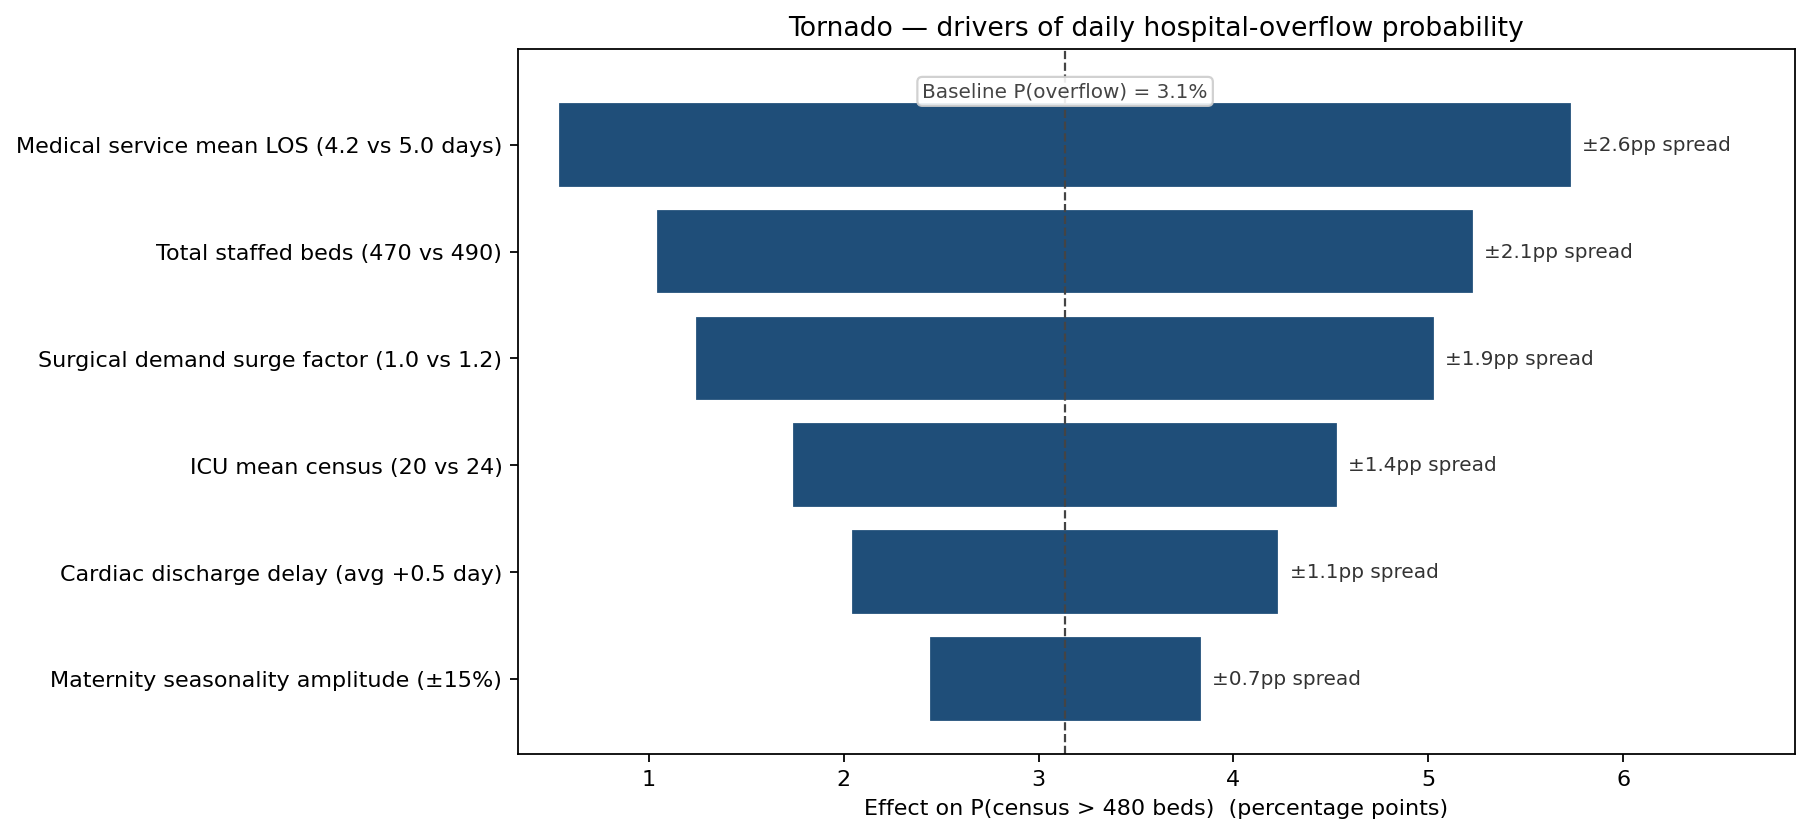
The single biggest mover is Medical service mean LOS: shaving the average length of stay from 5.0 to 4.2 days drops the overflow probability by ~2.6 percentage points — a large relative move against a ~3% baseline. Total staffed beds is second — opening 10 additional beds buys roughly 2 percentage points. Surgical demand surge sits third, ahead of ICU mean census. That ranking is what told the operations COO that the highest-leverage spend was a discharge-acceleration program for the Medical service, not a capital project to add ICU beds.
Three allocation strategies, one demand stream
The simulation re-evaluates allocation under common random numbers — every strategy is tested against the same 100,000 demand draws, so the comparison reflects strategy difference, not sampling noise.
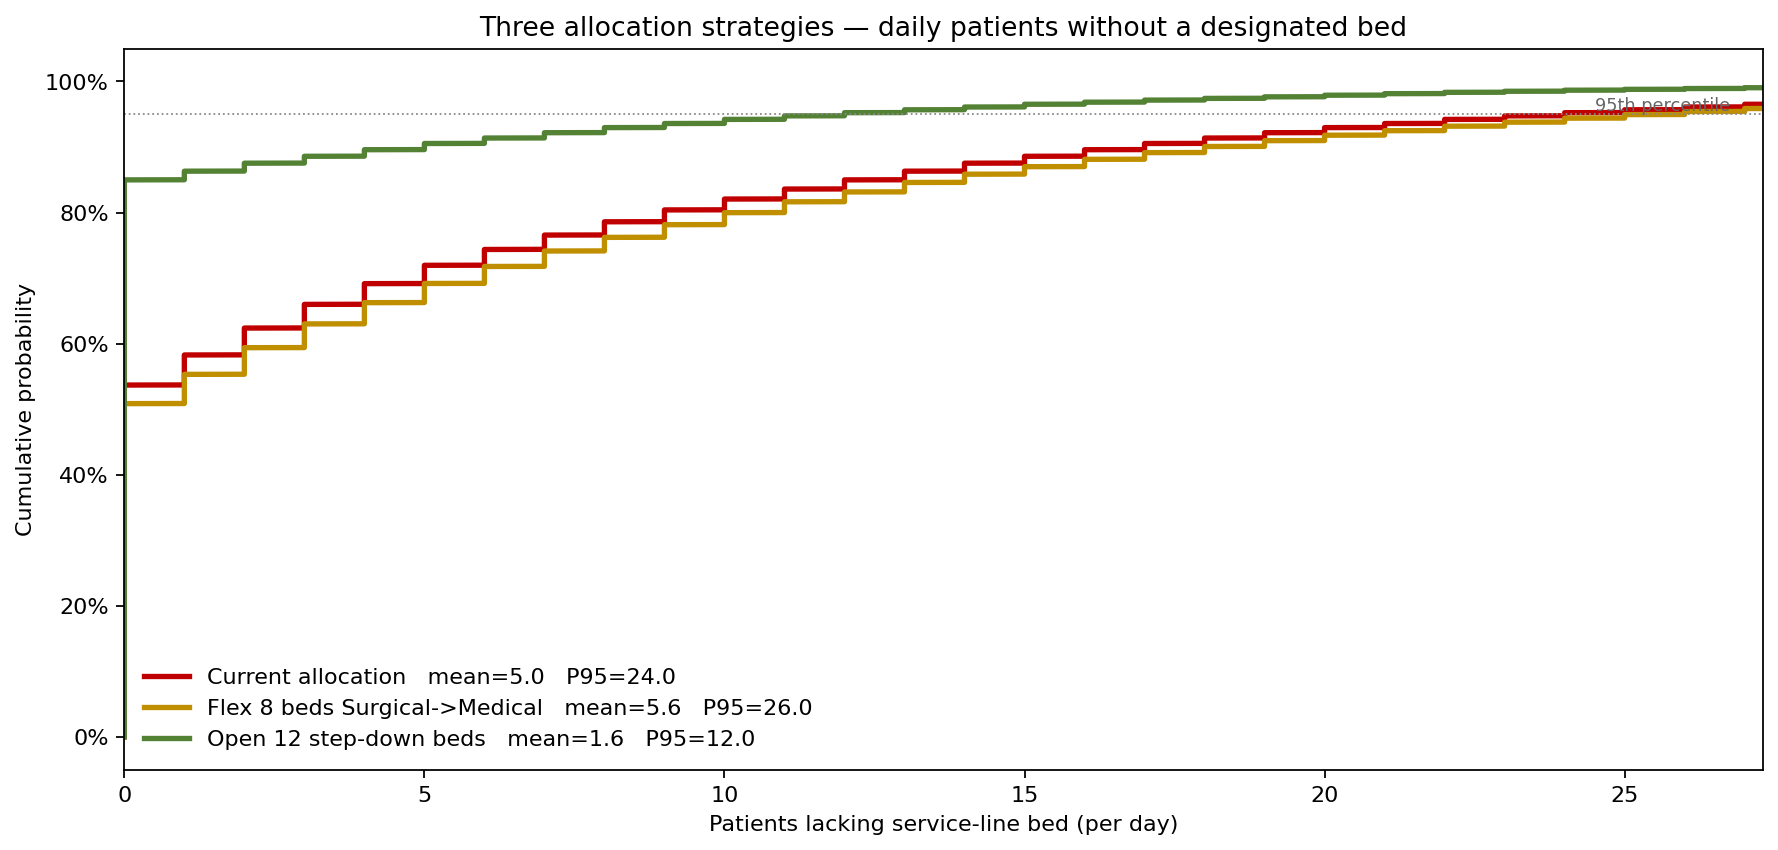
Strategy A (today) leaves ~24 patients per day at the 95th percentile without a designated service-line bed. Flexing 8 beds from Surgical to Medical (Strategy B) barely moves the P95 — it actually edges it up to ~26, because Surgical demand has a fat tail of its own that the flex exposes. Opening 12 step-down beds (Strategy C) cuts the P95 shortage to about 12 patients/day and the P99 from 39 to 27. The step-down approach is more expensive at standing capacity but materially better in the tail, which is exactly where overflow drives the worst patient-safety incidents.
A flex-staffing rule for ICU
The same simulation evaluated a forecast-triggered flex-staffing rule for the ICU: when the next-day forecast exceeds 30 patients, open up to 6 additional ICU beds with a pre-credentialed flex-pool nurse roster.
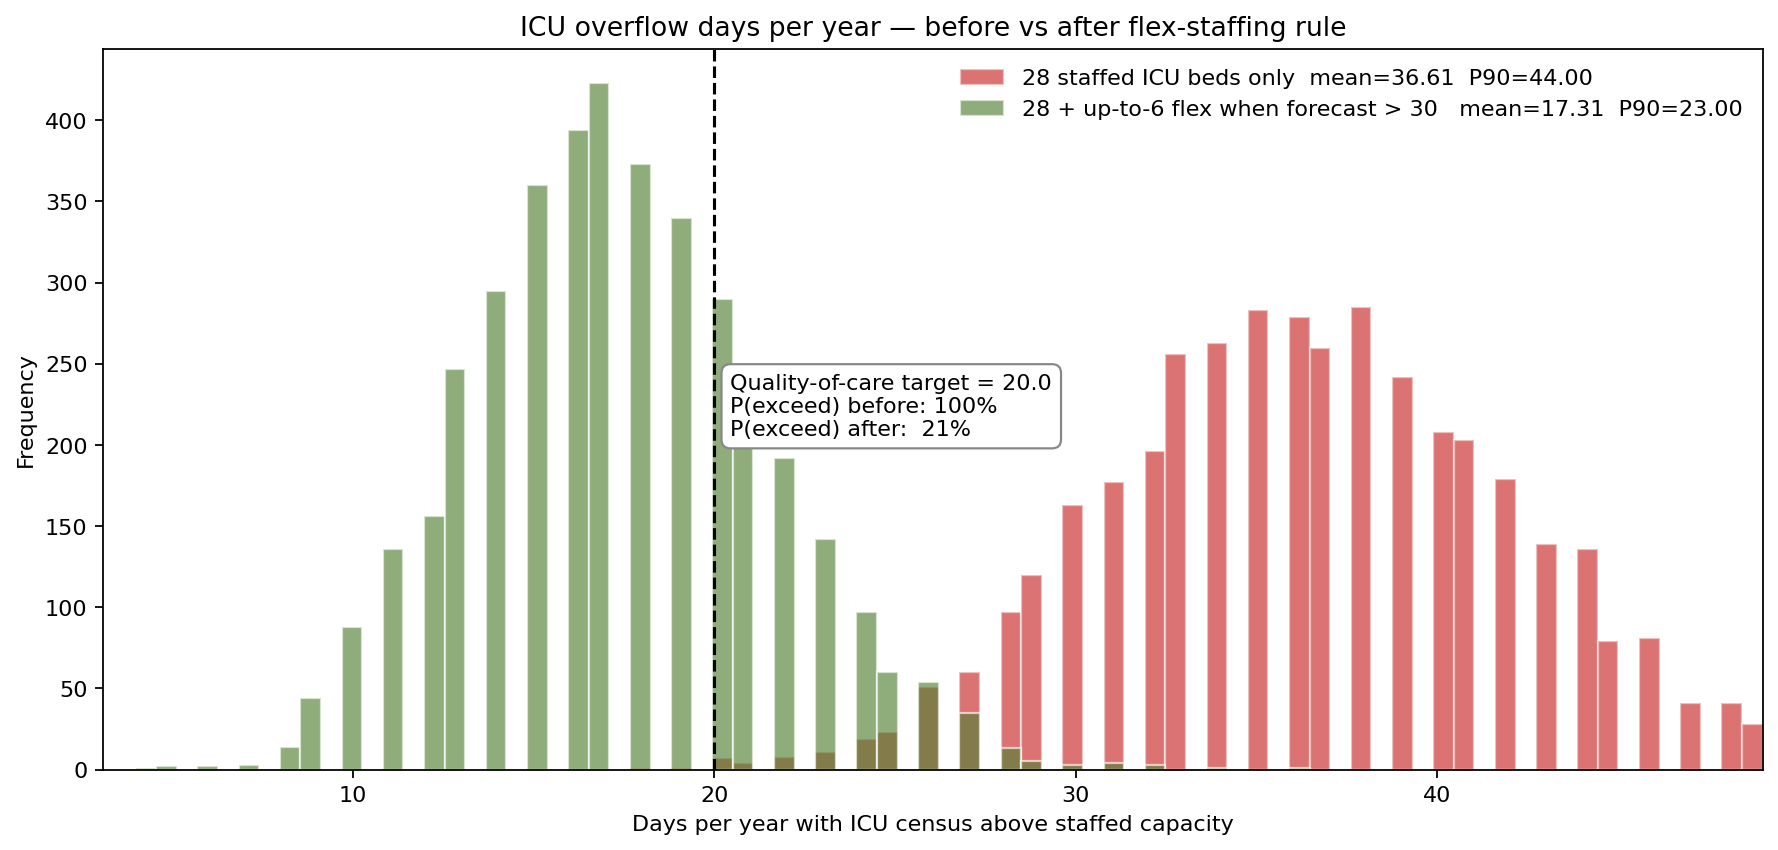
ICU overflow days fall from a mean of ~37 days/year to ~17 days/year, and the probability of exceeding the 20-day quality-of-care threshold drops from roughly 100% to about 21%. The marginal cost of the flex roster is $540,000/year; the alternative — staffing six additional ICU beds permanently — was costed at $2.1M/year and produced essentially the same risk-reduction profile. The simulation paid for itself in the first quarter of the next budget cycle.
What the model changed
- Discharge-acceleration program for Medical service funded as the highest-ROI item in the operating plan, targeting a 0.8-day LOS reduction worth ~2.6 percentage points of daily overflow probability.
- Step-down unit (12 beds) approved ahead of additional ICU build, because the simulation showed step-down beds catch the right tail of Cardiac+ICU joint demand more efficiently per dollar.
- ICU flex-staffing rule replaces a proposed permanent ICU expansion, saving an estimated $1.6M/year while delivering equivalent overflow reduction.
- OR scheduling rule tightened. Elective add-ons on days with predicted inpatient census > 460 are deferred — the simulation showed this rule lowers same-day cancellation cost while not affecting the 4-week elective-throughput target.
- Capacity-plan filings to the regional health authority now cite simulated P95/P99 census and per-service shortage metrics rather than annual averages.
ModelRisk Functionality Used
- Per-service Negative Binomial census models capturing the 1.0×–2.6× over-dispersion the historical data shows — replacing the implicit Poisson assumption in the deterministic LP.
- 100,000-iteration aggregation of service-line draws to total daily census, producing the full census distribution rather than a single utilization figure.
- Scenario engine under common random numbers so the three allocation strategies are compared on identical demand streams, isolating strategy effect from sampling noise.
- Tornado ranking that placed Medical LOS and total staffed beds above ICU mean census, redirecting capital spend away from an ICU build to a discharge-acceleration program.
- Forecast-conditioned flex-staffing simulation for the ICU, quantifying the trade-off between $540K/year flex pool and $2.1M/year permanent staffing for equivalent overflow reduction.
- Annual aggregation by re-sampling daily simulation draws into 4,000 simulated years to get the overflow-days-per-year distribution used in the quality-of-care threshold comparison.
A hospital running at the deterministic mean is a hospital one bad week from a capacity crisis. ModelRisk turns that hidden tail into a number the COO can buy down with the cheapest available unit of capacity — which is rarely the unit the deterministic LP would have spent on first.