

Industry: Healthcare and Epidemiology
Product: ModelRisk
Application: Health outcomes — cost-effectiveness analysis
Is a $28,000-a-Year Biologic Cost-Effective? The Question Has a Distribution
Health-technology assessment bodies — NICE in the UK, ICER in the US, CADTH in Canada — set willingness-to-pay thresholds around $50,000–$150,000 per quality-adjusted life year (QALY). A new biologic for moderate-to-severe psoriasis with an annual acquisition cost near $28,000 sits in the zone where reimbursement is decided by the probability the intervention is cost-effective at the threshold, not by a single deterministic ICER. The cost-effectiveness acceptability curve (CEAC) below is the chart NICE and ICER actually want to see — the entire probability-vs-threshold relationship — and on this biologic it tells a blunt story: at every conventional threshold the probability of cost-effectiveness is low, and only above roughly $274,000 per QALY does it cross 50%.
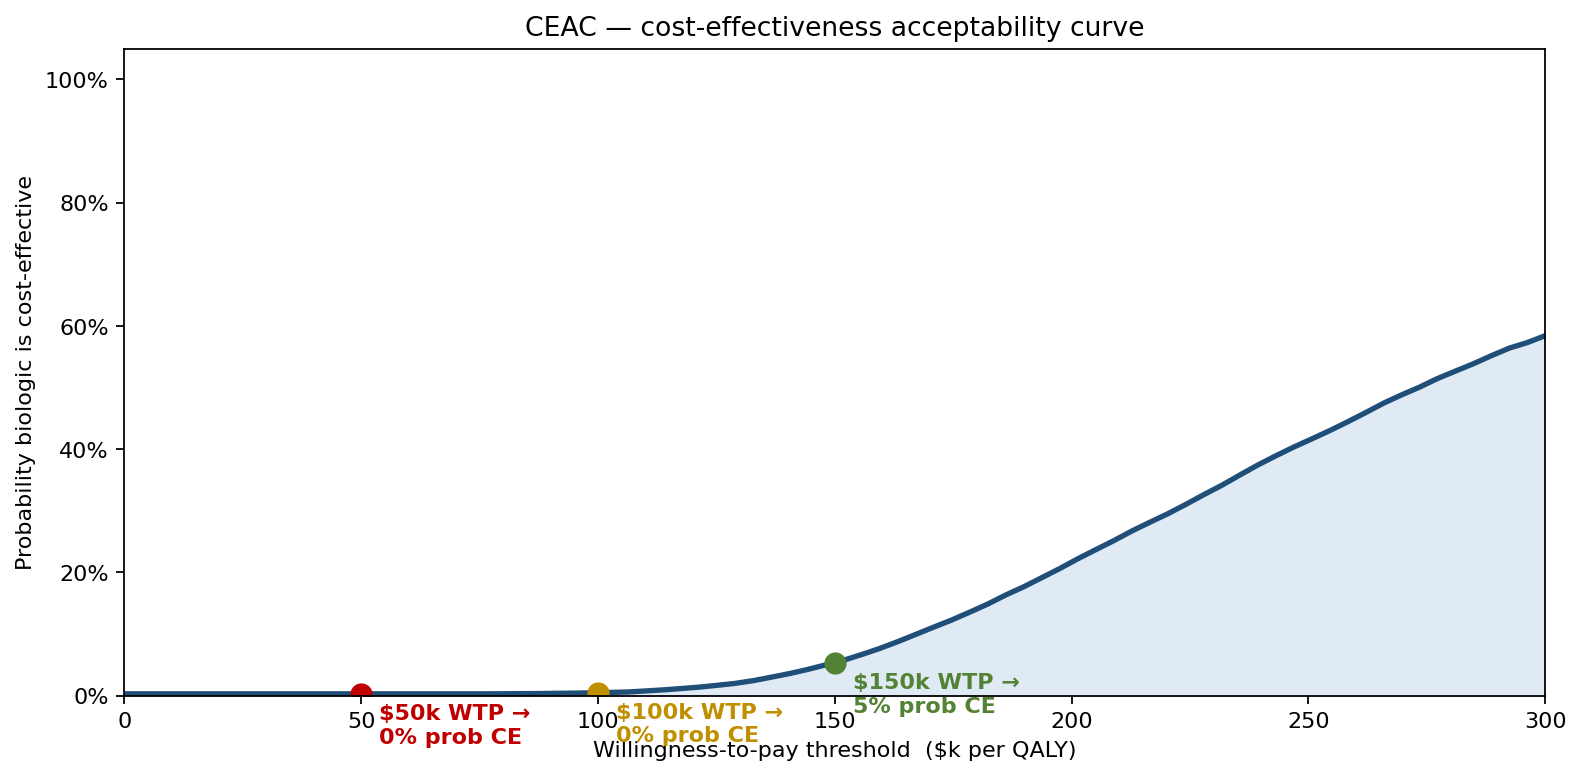
A health economics team built the probabilistic sensitivity analysis (PSA) for the new biologic in ModelRisk over a 10-year horizon, with parameter uncertainty on response rates, utility weights, costs and adverse-event burden. The mean ICER came out at $306,000 per QALY, with a median of $273,000 — far above the $50k–$150k decision band. The Monte Carlo PSA showed the probability of cost-effectiveness was effectively 0% at $50k, 0% at $100k, and just 5% at $150k. That is the verdict a point estimate would have obscured: at its current list price the biologic is not cost-effective at any conventional threshold, and the CEAC quantifies exactly how large a price concession the math demands.
Parameter priors for the PSA
PASI 75 response rate, treatment arm: Beta(76, 24) — mean 76%, 90% CI 67%–83%, calibrated from a Phase III pivotal trial. PASI 75 response rate, control (standard care): Beta(28, 72) — mean 28%, 90% CI 21%–35%, from real-world comparator data.
The Beta distribution is the only defensible choice for a response rate — bounded on [0, 1], conjugate to Binomial trial data, and allows the asymmetry that small-sample estimates always carry. A Normal here would let the simulator draw negative response rates.
Utility weight for responders: Normal(0.85, 0.04) clipped to [0, 1] — the standard EQ-5D-derived utility for a PASI 75 responder. Utility weight for non-responders: Normal(0.65, 0.06) clipped to [0, 1].
Annual treatment cost: LogNormal centered on $28,000 with σ_log = 0.15 — captures wholesale acquisition cost variation plus contract rebates. Annual standard-care cost: LogNormal centered on $3,200 with σ_log = 0.25 — wider relative uncertainty because comparator care is heterogeneous. Annual adverse-event cost (treatment only): LogNormal centered on $900 with σ_log = 0.5 — heavy-tailed because biologics carry rare severe-AE risk.
All costs and QALYs were discounted at 3% per year over the 10-year horizon, per UK and US health-economic guideline practice.
Twenty thousand PSA draws produced the joint distribution of incremental cost and incremental QALY per patient.
The CE plane — where the action is

Every point is one PSA draw. The x-axis is incremental QALY (positive in 99.7% of draws — the treatment is more effective); the y-axis is incremental cost (positive in 100% of draws — the treatment is more expensive). The three dashed rays are the willingness-to-pay thresholds: any point below a given ray is cost-effective at that threshold. The cloud sits high above all three rays: only 0.3% of draws fall below the $50k ray, and 95% fall above the $150k ray — not cost-effective at any conventional threshold. The treatment clearly works (mean incremental gain 0.85 QALY), but at this price the cost per QALY lands well outside the reimbursement band.
ICER distribution — the whole curve sits above the threshold band

The simulated ICER has a median of $273,000/QALY and a mean of $306,000/QALY — the mean sits above the median because the right tail dominates, a right-skew that comes from the LogNormal cost priors and the bounded-above utility weights. The distribution is decisive rather than borderline: there is a 78% probability the ICER exceeds $200,000/QALY and a 42% probability it exceeds $300,000/QALY. A deterministic point estimate near the median would have made the answer look merely "high"; the full distribution shows it is high with very little chance of being otherwise.
Reading the CEAC — what the curve demands
The CEAC at the top of this article reads: at $50k/QALY, probability of cost-effectiveness is effectively 0%; at $100k/QALY, still effectively 0%; at $150k/QALY, 5%. The probability does not reach 50% until a willingness-to-pay of roughly $274,000/QALY. The recommendation calculus follows directly: at the list price, no conventional threshold supports reimbursement — the question is not whether a price concession is needed but how large it must be to pull the curve into the decision band.
The biologic's manufacturer used the CEAC to frame the negotiation around price: because incremental cost is almost entirely drug-acquisition cost, the ICER scales nearly linearly with price, so closing the gap from a $273k median ICER to a $150k target implies a list-price reduction on the order of 45%. The manufacturer paired the concession analysis with a value-based contract structure that tied a portion of revenue to real-world PASI 75 rates relative to the Beta(76, 24) prior.
What actually drives the ICER
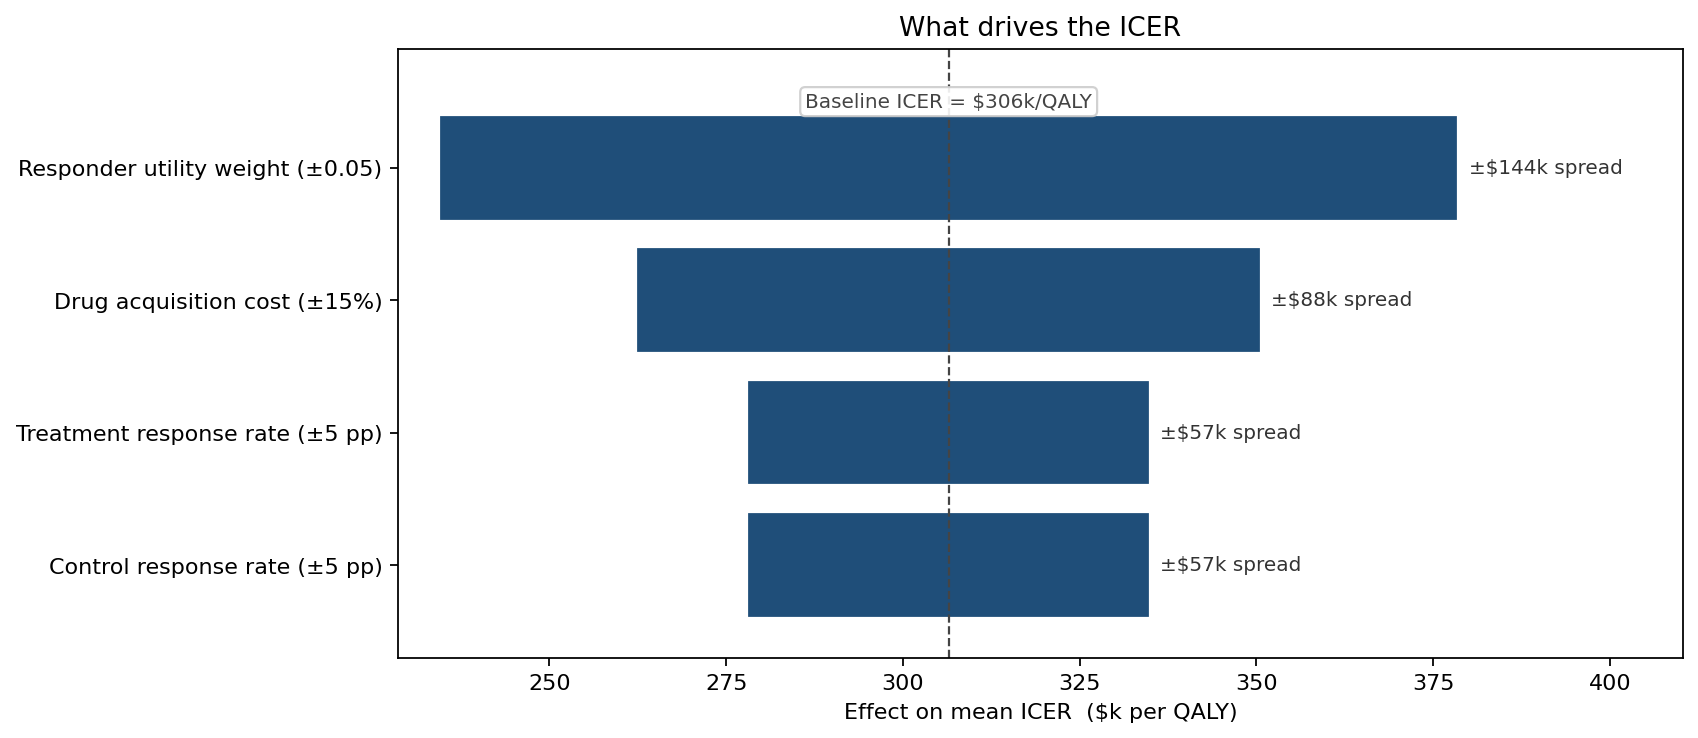
The responder utility weight has the biggest single effect on the ICER — a ±0.05 shift moves the mean ICER by roughly ±$72k/QALY, because utility scales the entire QALY denominator. Drug acquisition cost is second: a ±15% price change moves the ICER by roughly ±$44k/QALY. The treatment and control response rates come next, each worth about ±$28k/QALY for a ±5-percentage-point shift.
The implication for the manufacturer: drug price is the lever it actually controls, and a ±15% move on price is worth ±$44k/QALY — enough that a substantial concession is the only realistic route into the threshold band. The implication for the payer and the HTA committee: the utility weight is the single most influential evidence parameter, so tightening the EQ-5D utility estimate for responders is the highest-value analytic investment after the price negotiation.
What changed
- CEAC supplanted the single ICER in the reimbursement submission — the probabilistic framing made explicit that the biologic is not cost-effective at list price under any conventional threshold, and quantified the concession required.
- Price concession quantified — because the ICER scales nearly linearly with drug price, the simulator translated the $150k threshold into a roughly 45% list-price reduction, giving the manufacturer a defensible target for negotiation.
- Value-based contract structure tied a portion of revenue to real-world PASI 75 rates relative to the Beta(76, 24) prior, sharing downside if response fell short.
- Utility-evidence study commissioned to tighten the responder EQ-5D utility weight — the tornado made the case that the responder utility weight was the highest-marginal-value evidence parameter after the price concession.
ModelRisk functionality used
- Beta priors on response rates — bounded probabilities calibrated from trial data, with effective sample sizes that match the actual published trial denominators.
- Truncated Normal priors on utility weights with clip to [0, 1] — Normal alone allows utility > 1 (better than perfect health), which is unphysical.
- LogNormal cost priors for drug, comparator care and AE costs — appropriate for positive-only, right-skewed cost data.
- 3% discount rate applied to both cost and QALY streams over the 10-year horizon — the standard health-economic convention.
- 20,000-iteration PSA producing the joint (incremental cost, incremental QALY) distribution, the cost-effectiveness plane, the ICER distribution and the CEAC in one simulation pass.
- Tornado driver decomposition that ranked the responder utility weight and drug acquisition price as the two dominant ICER levers, directing both the evidence-refinement and negotiation strategy.
A single ICER answers "is it cost-effective on the central estimate?" — but reimbursement committees today ask "with what probability is it cost-effective at our threshold?" Monte Carlo simulation in ModelRisk is what makes the CEAC computable, the question askable, and the price-and-evidence negotiation defensible.